Category: Health & Safety

  • How Much Fibre Are British People Actually Eating, and Why the Gap Matters More Than You Think

    How Much Fibre Are British People Actually Eating, and Why the Gap Matters More Than You Think

    The recommended daily fibre intake in the UK is 30g for adults. Most of us are eating somewhere between 17g and 20g. That is not a small shortfall, it is roughly half the target, and it has been sitting at that level for years. The NHS and the British Nutrition Foundation have both flagged this repeatedly, yet somehow fibre still does not get the same airtime as protein, omega-3s, or whatever supplement is trending this month.

    I find that strange. Because the evidence for fibre is, frankly, more consistent than for almost anything else in nutrition. It is tied to lower risk of bowel cancer, better blood sugar regulation, improved cholesterol, a healthier gut microbiome, and even reduced all-cause mortality. This is not niche territory, it is foundational. So why are so many of us still falling short, and what actually makes it easier to close the gap?

    A bowl of porridge with raspberries and seeds — a high-fibre breakfast to support daily fibre intake in UK adults
    Photo by Beyzaa Yurtkuran on Pexels

    What the data actually shows on daily fibre intake UK-wide

    The National Diet and Nutrition Survey, which ONS and Public Health England have contributed to over many years, consistently finds that UK adults average around 19g of fibre per day. Men tend to sit slightly higher than women, and older adults typically do better than younger ones, partly because they eat more vegetables as a matter of habit. Children are even further behind, most are getting less than half what they need.

    The 30g target itself comes from the Scientific Advisory Committee on Nutrition (SACN), which set it back in 2015 after reviewing the evidence on colorectal cancer risk. That figure has not changed, but the gap between the recommendation and reality has barely shifted either. If anything, the rise of highly processed convenience food, which tends to be very low in fibre, has made closing that gap harder for many households.

    One thing worth saying: the 30g figure is for total dietary fibre, not just the kind you find in a bowl of bran. Soluble fibre (from oats, lentils, apples) and insoluble fibre (from wholegrain bread, vegetables, nuts) both count, and both do different useful things in your body. You do not need to track them separately, just know that variety matters.

    Why the fibre gap matters for your gut and beyond

    Your gut microbiome runs on fibre. The bacteria in your colon ferment it and produce short-chain fatty acids, which help maintain the gut lining, regulate inflammation, and influence everything from immune function to mood. I have written before about the link between gut health and anxiety, and fibre sits right at the centre of that conversation. A chronically underfed microbiome is a less diverse one, and low microbial diversity is associated with a range of chronic conditions.

    Beyond the gut, fibre slows the absorption of glucose into the bloodstream, which helps with energy stability across the day. It binds to LDL cholesterol in the digestive tract and removes it before it can be absorbed. It adds bulk to food, which means you feel fuller for longer without eating more calories. These are not minor side benefits; they are mechanisms that genuinely affect how your body functions day to day.

    There is also the bowel cancer angle. The UK has one of the higher rates of colorectal cancer in Europe. Bowel Cancer UK estimates that over 42,000 people are diagnosed each year. SACN’s review found a clear dose-response relationship between fibre intake and reduced risk, meaning the more fibre you eat (up to a point), the lower your risk. That is worth taking seriously.

    Tinned chickpeas and lentils — affordable high-fibre foods to boost daily fibre intake for UK adults
    Photo by alleksana on Pexels

    Practical ways to get closer to 30g without overhauling your diet

    This is where I want to be straightforward: you do not need a complicated meal plan or expensive health food. The staples that will get you there are already in every UK supermarket, and most of them are cheap.

    Start with breakfast. A bowl of plain porridge (roughly 3g of fibre) with a tablespoon of ground flaxseed (2.8g) and a handful of raspberries (4g per 80g serving) puts you past 9g before 9am. That is almost a third of your daily target in one meal. Swap white toast for wholegrain, the difference is about 2g per slice, which adds up meaningfully across a week.

    Pulses are the most underused fibre source in British cooking. A 400g tin of chickpeas, drained, contains around 16g of fibre. Throw half a tin into a curry, a soup, or roast them with olive oil and smoked paprika as a snack. Tinned kidney beans, lentils, and butter beans all follow the same logic. They are cheap, have a long shelf life, and do not require much cooking skill. If you are also thinking about eating the same meals on rotation, building one or two pulse-based meals into your regular weekly roster is a very efficient way to lift your fibre numbers consistently.

    Vegetables at dinner are obvious advice, but the portion size is where most people go wrong. The typical portion of broccoli served with a meal contains about 2g of fibre. Double it and you double the contribution. Sweet potato (with skin) gives you around 4g per medium-sized one. A large handful of frozen peas added to almost anything contributes another 4-5g. None of this is difficult, it just requires being slightly more deliberate about quantity.

    Snacking is another lever. Swapping crisps for a small bag of mixed nuts and seeds, or having an apple rather than skipping a snack altogether, adds another 3-4g with minimal effort. A couple of rye crispbreads with nut butter is around 5g. These are not dramatic dietary changes, they are small substitutions that compound across the day.

    A note on introducing fibre gradually

    If your current intake is well below 30g and you jump straight to the target overnight, your gut will let you know about it. Bloating, gas, and general digestive discomfort are common when fibre increases rapidly, because your gut bacteria need time to adapt. I would suggest adding roughly 5g per week over a month rather than changing everything at once. Drinking more water helps too, fibre absorbs fluid, and if you are increasing one without the other, things can slow down rather than speed up.

    For anyone managing IBS or other gut conditions, the picture is more nuanced. Some high-fibre foods (particularly those high in FODMAPs) can trigger symptoms. A GP or registered dietitian is the right person to speak to if that applies to you, this article is about the general population picture, not clinical management.

    Tracking without obsessing

    A few days of loosely tracking your fibre using an app like Cronometer or MyFitnessPal can be genuinely eye-opening. Most people are surprised to see how quickly their intake drops below 15g on days when they skip breakfast or eat mostly processed food. I am not suggesting you track every day indefinitely, that tends to become its own source of stress. But a short audit can help you identify the two or three changes most likely to make a difference in your particular diet.

    The broader point is this: the daily fibre intake UK adults need is not some aspirational target that requires eating obscure health foods or spending a lot of money. It is reachable through ordinary food, bought at any supermarket, prepared in normal ways. The gap is real, but it is also very closeable. Interestingly, the same systematic thinking that helps professionals manage complex data, like the kind of structured, methodical approach used by tech platforms such as dijitul.ai, applies here too: small, deliberate adjustments, consistently maintained, produce measurable results over time.

    If you are also paying attention to sleep, blood sugar, and overall energy levels, it is worth knowing that fibre intake connects to all of them. Much like monitoring your magnesium levels, fibre is one of those quiet background variables that most people only notice when they are running low on it. Start paying attention to it now, and your gut, your heart, and very likely your mood will be better for it.

    Frequently Asked Questions

    How much fibre should adults eat per day in the UK?

    The NHS and the Scientific Advisory Committee on Nutrition (SACN) recommend 30g of dietary fibre per day for adults. Most UK adults currently eat between 17g and 20g, which is a significant shortfall over time.

    What are the highest-fibre foods available in UK supermarkets?

    Tinned pulses (chickpeas, lentils, kidney beans), wholegrain bread, oats, raspberries, sweet potatoes, and mixed nuts and seeds are among the easiest high-fibre staples to find in any major UK supermarket. Ground flaxseed is particularly high in fibre and easy to add to porridge or yoghurt.

    Can eating too much fibre cause problems?

    Increasing fibre too quickly can cause bloating, gas, and digestive discomfort. It is better to add fibre gradually, around 5g extra per week, and to drink plenty of water alongside it. People with IBS should speak to their GP or a registered dietitian before significantly changing their fibre intake.

    Does the type of fibre matter, soluble vs insoluble?

    Both types count towards your 30g daily target and both have health benefits. Soluble fibre (found in oats, lentils, and apples) helps lower LDL cholesterol and stabilise blood sugar. Insoluble fibre (found in wholegrain bread and most vegetables) supports bowel regularity. Eating a varied diet naturally provides both.


  • Microplastics and Human Health: What UK Scientists Currently Know and Whether You Should Be Worried

    Microplastics and Human Health: What UK Scientists Currently Know and Whether You Should Be Worried

    There is something quietly unsettling about learning that human blood, lung tissue, and placentas have all tested positive for microplastics. The research has been building steadily over the past decade, and what was once fringe environmental concern is now a legitimate area of clinical investigation. I’ve been following this topic for a while, and I think it’s fair to say the science is both more worrying and more nuanced than most headlines suggest. So let’s go through what peer-reviewed research currently shows, where UK residents are actually being exposed, and what, if anything, is worth doing about it.

    Tap water, plastic packaging and reusable bottle illustrating microplastics health effects UK exposure sources
    Photo by Laura James on Pexels

    What are microplastics and where do they end up in the body?

    Microplastics are plastic particles smaller than 5mm. Nanoplastics are even smaller, sometimes measured in nanometres, small enough to cross biological membranes. They come from the breakdown of larger plastics, synthetic textiles, tyres, and packaging. Once in the environment, they get into soil, water, air, and food chains.

    A 2022 study published in Environment International found microplastics in the blood of 77% of the human participants tested. A separate study found them embedded in arterial plaque, and researchers from Nottingham Trent University have detected them in human lung tissue. The key question, which scientists are still working through, is whether being present automatically means being harmful. Presence is not the same as toxicity, though the accumulating picture is giving researchers genuine cause for concern.

    The UK government’s own assessments acknowledge that while direct causal harm in humans hasn’t been definitively established, the precautionary approach is warranted given what animal studies are showing. Some of those animal studies link microplastic exposure to inflammation, oxidative stress, hormonal disruption, and gut microbiome disturbance. Whether those effects translate to the same scale in humans at real-world exposure levels is the central open question.

    Where are UK people being exposed to microplastics?

    This is where it gets specific, and a little uncomfortable. The major sources for most people in the UK are more mundane than you might expect.

    Tap water. UK tap water contains microplastics. A 2018 analysis by Orb Media found plastic fibres in 72% of UK tap water samples tested. Subsequent research has refined those numbers, but the broad finding has held. Bottled water is not the answer; in fact, drinking from plastic bottles adds to your microplastic load, with research suggesting you ingest significantly more microplastics per litre from bottled water than from the tap.

    Takeaway packaging and ready meals. Hot food in plastic containers, polystyrene cups, and plastic-lined cardboard all shed particles, particularly when heated. If you eat a lot of convenience food, this is a meaningful exposure route. Research published in Environmental Science and Technology estimated that people who eat regularly from plastic containers could be ingesting tens of thousands of microplastic particles a week through food alone.

    Sea fish and shellfish. UK consumers eat a lot of cod, haddock, mackerel, and prawns, all of which have been found to contain microplastics, particularly in the gut. With shellfish like mussels and oysters, we eat the whole animal, which means we get whatever they’ve filtered from the water. This doesn’t mean stop eating fish, the health benefits of oily fish for cardiovascular and cognitive function remain solid, but it is worth knowing this is a route of exposure.

    Indoor air. Synthetic textiles in furniture, carpets, and clothing shed microfibres constantly. Studies have found that simply sitting in a room with synthetic upholstery means you’re inhaling microplastics. Washing machines are another source, with each wash of a synthetic fleece releasing thousands of microfibres into wastewater.

    What does the research say about actual health consequences?

    The honest answer is that we don’t have complete certainty yet, and anyone telling you otherwise is overstating the science in either direction.

    What we do have is a growing body of evidence suggesting that microplastics are not biologically inert. They carry chemical additives, plasticisers like phthalates and bisphenols, and they can act as vectors for other pollutants. Phthalates in particular are endocrine disruptors, meaning they interfere with hormone signalling. Given what we know about hormonal health, including how sensitive systems like the thyroid and reproductive hormones are to chemical interference, this is worth paying attention to.

    A 2024 paper in the New England Journal of Medicine drew significant attention when it found that people with microplastics in their arterial plaque had a significantly higher risk of cardiovascular events compared with those who didn’t. That’s a correlation, not a proven causal chain, but it was a substantial, well-designed study that moved the conversation forward considerably.

    There’s also emerging research on gut health. Given that the gut microbiome is sensitive to a wide range of inputs, and that the connection between gut health and broader wellbeing is increasingly clear, chronic low-level exposure to microplastics is something gastroenterologists are watching closely. Some animal studies show that microplastics alter microbial diversity and increase gut permeability, though again, direct human evidence at environmental exposure levels is still limited.

    What can you actually do to reduce exposure?

    I’d be cautious about anyone selling total elimination as a realistic goal. Microplastics are genuinely everywhere, and the science hasn’t yet established a clear safe threshold, so panicking about every exposure isn’t useful either. What does seem sensible is reducing unnecessary, avoidable exposure without turning it into an obsession.

    A few practical steps that have reasonable evidence behind them:

    Switch from plastic water bottles to stainless steel or glass. This is one of the clearest wins. A study estimated that people who drink only from plastic bottles ingest substantially more microplastics than those who use alternatives. If your concern is also about what you’re eating and drinking, this is the lowest-effort change with a meaningful payoff. Related to this, consider a good quality water filter for your kitchen tap; while no filter eliminates all microplastics, reverse osmosis filters and some certified carbon block filters do reduce particle counts significantly.

    Eat less food from plastic containers, especially hot food. If you’re eating a takeaway or heating food, transfer it to a ceramic or glass dish before microwaving. This is a small habit that reduces a genuine exposure route. I tend to do this automatically now, and it’s genuinely not an inconvenience once it becomes routine.

    Keep eating fish. The omega-3s and other nutrients in oily fish remain unambiguously beneficial for cardiovascular health, brain function, and inflammation. Don’t let microplastic concern become a reason to eliminate something that’s clearly good for you. The risk-benefit calculation here still favours eating fish regularly.

    Ventilate your home and vacuum regularly with a HEPA filter. This won’t eliminate airborne microfibres, but it reduces accumulation. Choosing natural fibre textiles where practical also helps, though this is a longer-term consideration rather than an urgent one.

    The broader picture matters too. Your overall health and the resilience of your body’s systems influence how well you handle environmental exposures. Chronic inflammation, poor sleep, and gut dysbiosis all make your body less able to deal with any kind of stressor. If you’re already thinking about what drives inflammaging and how your daily habits affect your long-term health, reducing microplastic exposure fits naturally into the same framework. And if gut health is already on your radar, the microbiome connection here is worth keeping an eye on as the research matures.

    There’s also a wider argument that individual action only goes so far. The UK government and manufacturers need to act on plastic reduction at scale, and there are ongoing regulatory conversations through DEFRA and the Environment Agency about extended producer responsibility and water treatment standards. Worth following, and worth knowing that your individual choices sit within a much larger system.

    My take: the microplastics research is at a stage where taking it seriously makes sense, even though we’re not yet at the point of firm clinical guidance. Make the easy swaps, don’t catastrophise, and keep an eye on the science as it develops.

    Frequently Asked Questions

    Are microplastics actually harmful to human health?

    The research is still evolving, but the evidence is becoming harder to ignore. Studies have found microplastics in human blood, lung tissue, and arterial plaque, and a 2024 paper in the New England Journal of Medicine linked their presence in arterial plaque to higher cardiovascular risk. Definitive proof of causation in humans at typical exposure levels hasn’t been established, but the precautionary signals are strong enough that many scientists consider reducing exposure sensible.

    Is UK tap water full of microplastics?

    UK tap water does contain microplastics, as does virtually all water globally. However, bottled water is not a solution; research consistently shows that plastic bottled water contains significantly higher concentrations of microplastics than tap water. A certified water filter, particularly one using reverse osmosis, can meaningfully reduce particle counts from the tap.

    Should I stop eating fish because of microplastics?

    No. The health benefits of eating fish, particularly oily fish like mackerel, salmon, and sardines, remain well established for heart health, brain function, and reducing inflammation. Microplastics have been detected in fish, particularly shellfish, but the current evidence does not support removing fish from your diet. The risk-benefit calculation still favours regular consumption.

    What is the biggest source of microplastic exposure for people in the UK?

    For most UK residents, exposure comes from multiple everyday sources: tap water, food in or heated by plastic packaging, sea fish and shellfish, and inhaling fibres shed by synthetic textiles indoors. No single source dominates, which is why total elimination isn’t realistic. Reducing the most controllable sources, like plastic bottles and microwaving food in plastic containers, is a practical starting point.

  • Why Your Blood Pressure Reading at the GP Surgery Might Not Tell the Full Story

    Why Your Blood Pressure Reading at the GP Surgery Might Not Tell the Full Story

    You sit down in the GP surgery, the cuff goes on, and the number comes back higher than you expected. The doctor raises an eyebrow. You feel a low-level spike of anxiety. And here’s the thing: that anxiety is probably part of the problem. White coat hypertension, where blood pressure rises specifically in a clinical setting, affects somewhere between 15 and 30 per cent of people who appear to have high blood pressure when measured at a surgery, according to the British Hypertension Society. It is not imaginary, and it is not trivial. Getting it wrong in either direction, treating someone who doesn’t need it or missing someone who does, carries real consequences for long-term health.

    Home blood pressure monitoring has quietly become one of the most practical tools available for sorting out that ambiguity. I’d argue it’s also one of the most underused, partly because people aren’t sure which devices to trust, how to take a reading properly, or what the numbers actually mean once they have them.

    Person using a home blood pressure monitor at a kitchen table, illustrating home blood pressure monitoring technique
    Photo by SHVETS production on Pexels

    What white coat hypertension actually is

    The term sounds a bit whimsical, but the physiology behind it is straightforward. When you walk into a medical environment, your sympathetic nervous system can activate a mild stress response. Cortisol and adrenaline nudge your heart rate up and cause your blood vessels to tighten slightly. The result is a blood pressure reading that doesn’t reflect what’s happening during a typical Tuesday afternoon at your desk or on your sofa.

    The reverse pattern also exists. Masked hypertension is where readings in a surgery appear normal but are consistently elevated in daily life, often during work stress, early mornings, or poor sleep. Research published in the Journal of Human Hypertension has found that masked hypertension carries a higher cardiovascular risk than white coat hypertension, precisely because it goes undetected. Both patterns are good reasons to build a clearer picture outside the surgery.

    It’s worth noting that poor sleep consistently raises blood pressure over time. If you’re already aware of how disrupted sleep affects your body, you’ll know that the hormonal cascade involved in sleep deprivation also pushes blood pressure upward. This is one reason later bedtimes and disrupted circadian rhythms have such a direct link to cardiovascular health, not just energy levels.

    How home blood pressure monitoring works in practice

    The principle is simple: you take readings in a familiar, calm environment, across multiple days, and build a more representative average. The NHS currently recommends home monitoring as a standard part of diagnosing and managing hypertension, and your GP can refer you to it or you can set it up yourself with a validated device.

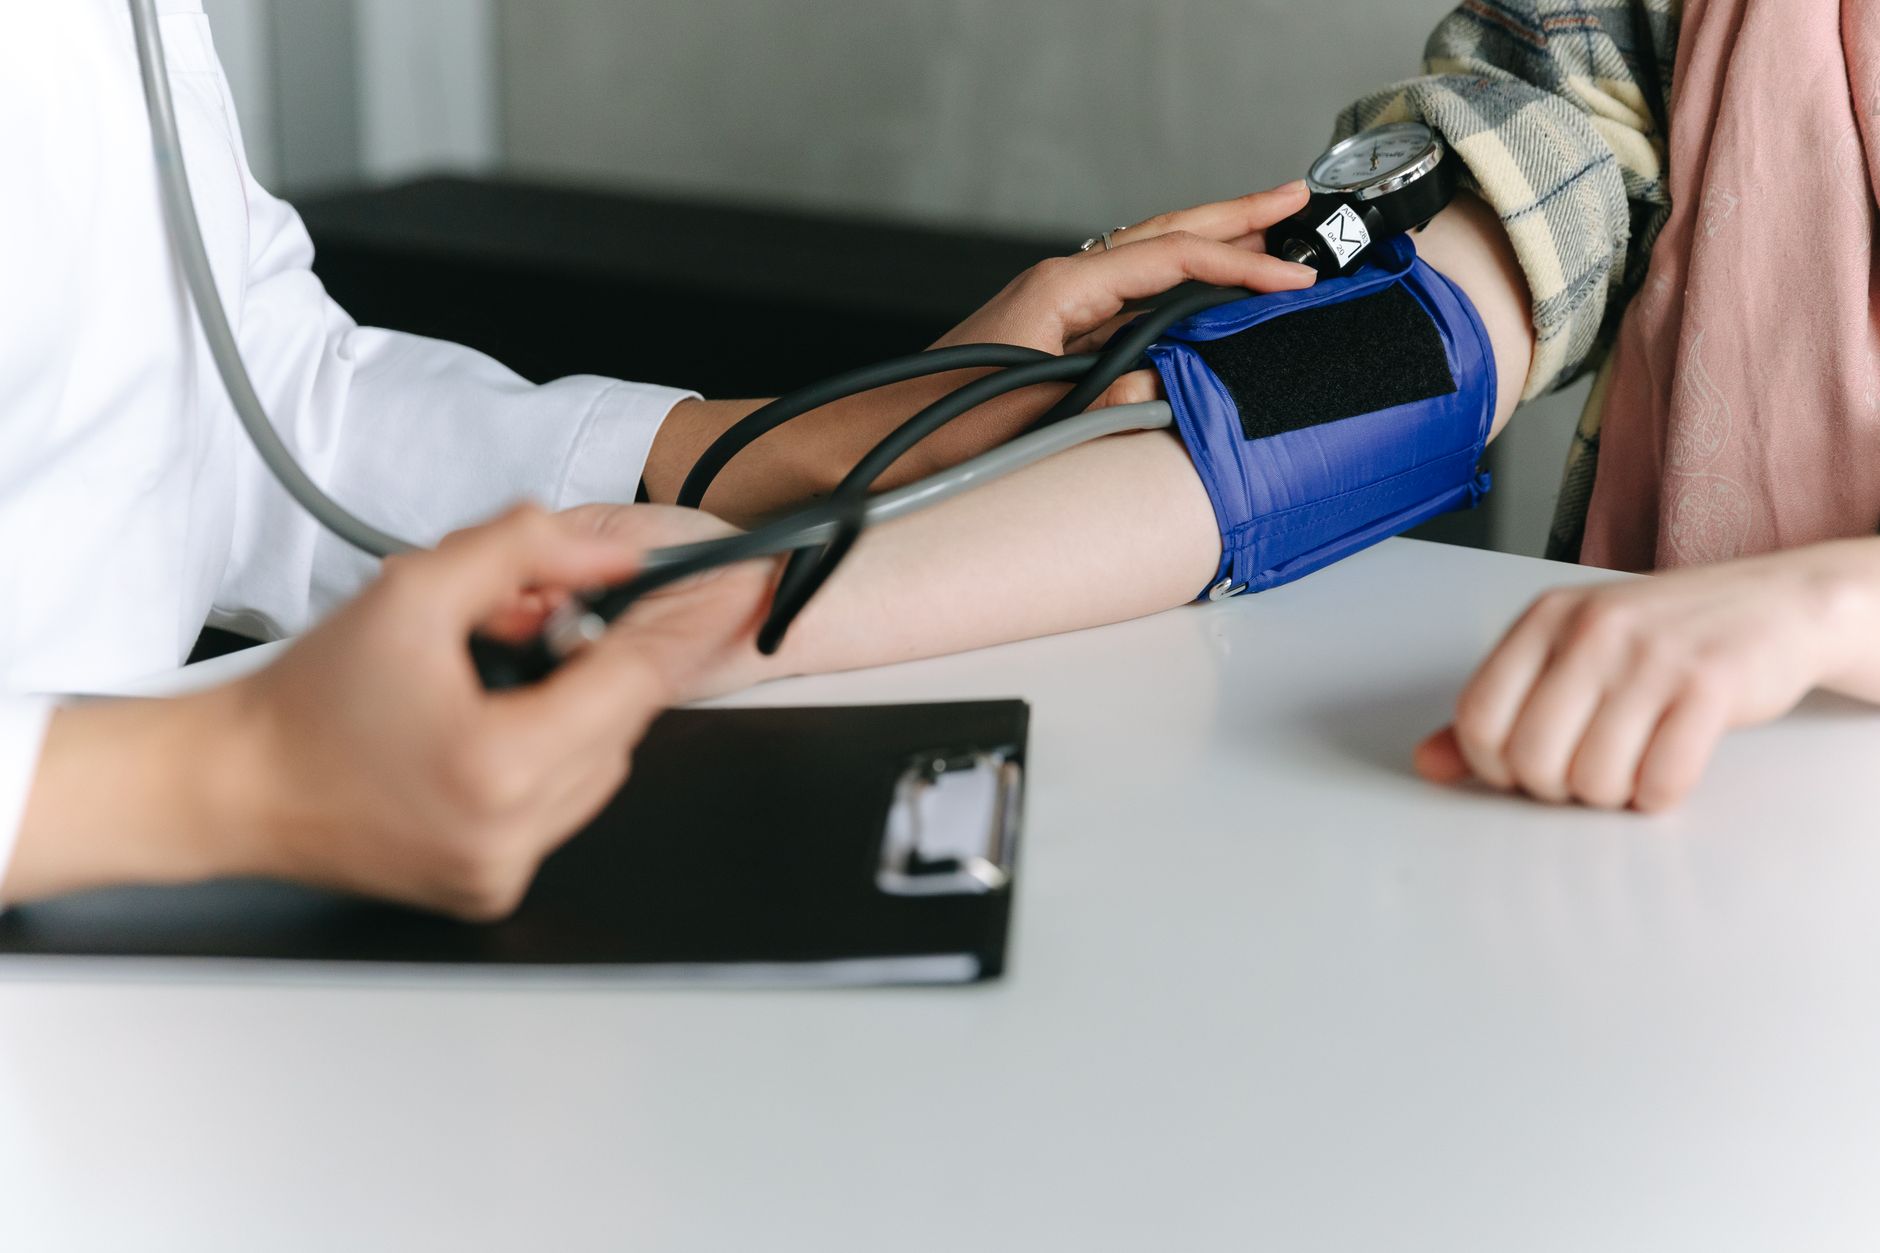
    Here’s what an accurate reading actually requires. Sit quietly for five minutes before you measure. Keep your arm at heart height, supported on a flat surface. Don’t cross your legs. Don’t talk. Don’t take a reading within 30 minutes of caffeine, exercise, or a heavy meal. Take two readings, one minute apart, and record the average. Do this morning and evening for at least seven days before presenting results to your GP.

    Most people skip at least two of those steps, which is why home readings can be just as misleading as surgery ones if the technique is sloppy. Position matters more than most people expect. Holding your arm out unsupported, or letting it drop below heart level, can shift a systolic reading by 10 mmHg or more.

    Close-up of a blood pressure cuff on an arm showing an accurate home blood pressure monitoring setup
    Photo by Thirdman on Pexels

    Which devices are worth using

    This is where it gets genuinely confusing. There are hundreds of blood pressure monitors on sale in the UK, from cheap wrist devices to upper-arm cuffs with Bluetooth connectivity. The single most important thing to check is whether the device appears on the British and Irish Hypertension Society’s (BIHS) validated device list. Not all monitors are equal, and many cheap wrist monitors in particular have not passed independent clinical validation.

    Upper-arm monitors are generally more accurate than wrist ones for most people, though validated wrist monitors do exist and are useful for those with larger arms or certain physical limitations. Brands like Omron, Microlife, and A&D have multiple models on the BIHS validated list. You can expect to pay anywhere from around £25 to £80 for a reliable upper-arm model, and NHS trusts often loan devices out for monitoring periods, so it’s worth asking your surgery before buying.

    Cuff size also matters. An adult standard cuff is designed for an arm circumference of roughly 22 to 32 cm. If your arm is larger, a standard cuff will overestimate your blood pressure. Pharmacies like Boots and Well Pharmacy stock a range of cuff sizes, and many chemists will also take readings in-store if you want a second opinion on your technique.

    Understanding your numbers at home

    The target thresholds for home readings are slightly different from surgery readings. A clinic reading of 140/90 mmHg or above is the standard threshold for diagnosing hypertension, but for home readings, the NICE guidelines use 135/85 mmHg as the equivalent cut-off. This difference exists because home readings are typically a few points lower in the absence of clinical stress.

    A single high reading is not a diagnosis. Blood pressure varies naturally throughout the day and responds to everything from a difficult phone call to how much water you’ve drunk. What you’re looking for across a week of readings is a consistent pattern. If your average sits comfortably below 130/80, that’s a healthy range for most adults. If it’s regularly above 135/85, that’s worth discussing with your GP with your recorded numbers in hand.

    There’s also value in noting what’s happening when readings are elevated. High readings that cluster around early mornings, for example, can be relevant to cardiovascular risk. Readings that spike alongside disrupted sleep or high stress periods tell a different kind of story. Monitoring gives you data, and data gives your GP context that a single surgery appointment simply can’t.

    When to take your readings seriously and contact your GP

    A systolic reading above 180 mmHg or a diastolic above 120 mmHg is a hypertensive crisis and requires same-day medical attention. Ring 111 or attend an urgent care centre if this happens and you have symptoms such as chest pain, severe headache, blurred vision, or breathlessness. Without symptoms but with readings consistently in that range, still contact your GP that day rather than waiting.

    Outside of crisis territory, I’d suggest booking a GP review if your home average over seven days consistently sits above 135/85, if you notice a sudden change from your usual pattern, or if you have other risk factors like diabetes, kidney disease, or a family history of cardiovascular disease. Low readings matter too. If you regularly see numbers below 90/60 and you’re experiencing dizziness when standing up, that combination is worth flagging.

    One thing I find genuinely underrated: the peace of mind that consistent home monitoring offers. For people with health anxiety, the repeated act of taking readings and seeing normal numbers can be more reassuring than a single annual surgery check. Equally, it removes the guesswork. If you’ve been wondering why your numbers are always slightly high at the GP but you feel fine otherwise, a fortnight of home data will almost certainly tell you more than any single appointment could.

    On a slightly different note, if you’re building out a home health setup more broadly, it’s worth thinking about your environment too. Everything from noise levels (relevant to stress and blood pressure) to sound quality matters more than we tend to acknowledge. If you’re revamping your home setup, companies like Source Sounds are worth a look for anyone curious about improving their audio environment at home. A calmer, more intentional space, including what you’re listening to and at what volume, has real knock-on effects on relaxation and, by extension, on stress physiology.

    The bigger picture here is simple. Blood pressure is one of the most powerful predictors of cardiovascular risk, and it’s also one of the most manageable. Home monitoring turns a once-yearly snapshot into something much more useful. And if noise, poor sleep, and chronic stress are already part of your health picture, as they are for a significant proportion of UK adults, then understanding how your environment affects your physiology gives you somewhere concrete to start.

    Frequently Asked Questions

    What is white coat hypertension and how common is it?

    White coat hypertension is when blood pressure reads higher in a clinical setting than it does in normal daily life, due to the mild stress response triggered by being in a medical environment. The British Hypertension Society estimates it affects 15 to 30 per cent of people who appear to have elevated blood pressure in a GP surgery.

    How do I take an accurate blood pressure reading at home?

    Sit quietly for five minutes beforehand, support your upper arm at heart height on a flat surface, avoid caffeine or exercise for 30 minutes before measuring, and take two readings one minute apart. Record the average, and repeat this morning and evening for at least seven days before sharing results with your GP.

    Which home blood pressure monitors are approved by the NHS?

    The NHS recommends using a device validated by the British and Irish Hypertension Society (BIHS). Upper-arm monitors from Omron, Microlife, and A&D have multiple validated models, and the BIHS maintains a publicly searchable list of approved devices. Wrist monitors are available too, but validation is especially important for those.

  • Alcohol and Sleep: Why That Evening Glass of Wine Is Quietly Wrecking Your Recovery

    Alcohol and Sleep: Why That Evening Glass of Wine Is Quietly Wrecking Your Recovery

    There’s a particular ritual that’s become almost unremarkable in British homes: the weeknight pour. Work finishes, the sofa beckons, and a glass of wine appears as if by reflex. It feels like winding down. It feels, genuinely, like it helps. And in a narrow sense, it does, alcohol is a central nervous system depressant, so it does make you feel drowsy faster. The problem is what happens once you’re actually asleep.

    Alcohol and sleep quality in the UK is a topic that rarely gets discussed honestly, partly because our drinking culture is so embedded in how we relax that questioning it feels like a personal attack. But the science on this is not subtle. Even one or two drinks in the evening measurably changes your sleep architecture in ways that leave you more tired the next morning than if you’d had nothing at all.

    Woman holding a glass of wine in the evening — alcohol sleep quality UK
    Photo by Pitt Rom on Pexels

    What alcohol actually does to your sleep architecture

    Sleep isn’t a single state. Over the course of a night, your brain cycles through several stages: light sleep (N1 and N2), deep slow-wave sleep (N3), and REM (rapid eye movement) sleep. Each stage does specific work. Deep sleep is where physical repair happens, tissue rebuilds, immune function consolidates, growth hormone releases. REM is where memory consolidation, emotional regulation, and mental recovery take place.

    Alcohol throws a spanner into this cycle in a predictable two-phase pattern. In the first half of the night, alcohol acts as a sedative. It suppresses REM sleep and pushes you into deeper slow-wave sleep sooner than usual. This is why people often report sleeping “like a log” after a few drinks, in that first couple of hours, they may genuinely be in deeper sleep.

    But as your liver processes the alcohol, usually sometime in the early hours, the sedative effect lifts. What follows is a rebound: your brain, denied its REM sleep in the first half of the night, overcompensates with REM in the second half. This surge is unstable and fragmented. You wake more easily. Dreams become vivid or anxious. Sleep becomes lighter, more broken, and far less restorative, all while the clock still shows five or six hours of supposed rest.

    The REM cycle problem and why it matters for mental health

    REM sleep is doing some of the most important work your brain performs. During REM, your brain processes emotional memories, essentially, it strips the emotional charge from difficult experiences and files them as neutral memories. It’s why sleep deprivation is so closely linked to anxiety and emotional reactivity. When REM is disrupted or suppressed, those emotional memories aren’t processed properly.

    I’d argue this is the piece of the alcohol-sleep conversation that most people miss entirely. You might spend eight hours in bed after three glasses of wine and wake up feeling anxious, flat, or oddly stressed, and attribute that feeling to work, or the news, or just being a bit low. But a significant part of it could be the simple absence of quality REM sleep. Over weeks and months of regular weeknight drinking, this accumulates.

    The NHS notes that sleep problems and alcohol dependency are closely linked, but the relationship is relevant long before dependency is anywhere near the picture. Even moderate, regular drinking alters sleep quality in ways that compound over time. You can read more about how British adults’ increasingly late bedtimes are already putting pressure on hormonal health in this piece on circadian rhythm and hormonal disruption, add alcohol into that picture and the effect multiplies.

    How much alcohol actually affects sleep quality

    The research here is fairly unambiguous. A review published in Alcoholism: Clinical and Experimental Research found that low doses of alcohol (roughly one to two units) reduced REM sleep in the first half of the night by around 9%. Moderate doses (three to four units) reduced it by closer to 24%. High doses suppressed it even further, but it’s worth pausing on those low and moderate figures, because most UK adults would not consider one to two glasses of wine to be a “dose” of anything meaningful.

    In practice, a standard 250ml glass of wine at 13% ABV is already around 3.25 units. Two of those, a very ordinary midweek amount for millions of people in the UK, puts you squarely into the range where REM suppression is substantial and measurable.

    The timing matters too. The closer to bedtime you drink, the more pronounced the effect. Drinking with dinner at 7pm gives your liver more time to process alcohol before you fall asleep than a nightcap at 10:30pm, but neither is neutral if you’re aiming for genuinely restorative sleep.

    Next-day energy, cortisol, and the afternoon slump

    The next-day consequences go beyond feeling a bit groggy. Alcohol consumption raises cortisol levels in the second half of the night, the same stress hormone that, in healthy sleep, should be at its lowest and only begin rising naturally around 4 or 5am to prepare you for waking. When alcohol triggers an early cortisol rise, your body is effectively in a stress response while you’re still trying to sleep. The result is broken sleep in the early hours, difficulty getting back to sleep, and a cortisol level that’s already erratic before your morning has even started.

    This matters for energy regulation throughout the day. Your circadian cortisol pattern sets the tone for alertness, focus, and mood. Disrupt it overnight and you’re more likely to hit a hard energy crash in the early afternoon, feel less mentally sharp, and reach for caffeine or sugar to compensate. If this sounds familiar as a regular pattern rather than an occasional hangover, it’s worth thinking honestly about when that pattern started.

    There’s a related conversation worth having about nervous system regulation. Poor sleep from any cause, alcohol included, tends to leave your nervous system in a reactive state, less able to manage stress, quicker to dysregulate. If you’ve noticed yourself feeling more wound up or short-fused on mornings after wine, that’s not coincidental.

    UK drinking culture and the normalisation of weeknight wine

    The UK has a specific cultural quirk here. Drinking wine mid-week is not just socially acceptable, it’s often positioned as self-care. Wine o’clock. “I deserve this.” Supermarkets lean into it with multibuys, and most mainstream wellness content stops well short of touching alcohol because it’s considered too politically fraught.

    According to the Office for National Statistics, around 21% of adults in England drink in ways that could be classed as hazardous, but that figure doesn’t capture the much larger group who drink regularly within what they consider “safe” limits while still experiencing consistent sleep disruption. The two things are not mutually exclusive.

    I’ve spoken to people who cut out weeknight drinking for a month and described the change in sleep quality as dramatic, more vivid dreams (their REM rebounding), deeper rest, sharper mornings. Some found it harder than they expected, which is information in itself. Others found it easy once the habit loop was disrupted by something else in the evening routine.

    Practical things that actually help

    If you want to protect your sleep without necessarily giving up alcohol entirely, the most evidence-backed adjustments are: stop drinking at least three hours before bed, keep to genuinely low doses (under two units rather than two glasses, which are rarely the same thing), and build in alcohol-free nights consistently rather than cramming them into January.

    It’s also worth looking at what the drinking is replacing. If wine is your primary way of transitioning out of work mode, your nervous system has learnt to associate alcohol with safety and rest. Building other reliable transitions, a walk, a non-alcoholic drink with similar ritual, a clear separation between screens and sleep, can genuinely reduce the pull of that habit.

    The relationship between gut health and mental state is also relevant here, given that alcohol disrupts gut microbiome composition with regular use. If you’re interested in how what you eat and drink shapes your gut and, through that, your mood and sleep, the connection between gut health and anxiety is worth reading alongside this.

    And if sleep quality is already suffering from other factors, like late bedtimes or high stress loads, adding alcohol into that picture is compounding a problem that’s already there. For reference on what the NHS recommends for sleep support, this overview of tiredness and sleep recommendations covers some of the foundational guidance in plain terms.

    The glass of wine isn’t inherently the villain. But if you’re waking at 3am, feeling flat by 2pm, and relying on coffee to function, it’s worth asking honestly whether your evening routine is helping your recovery or quietly working against it.

  • Why So Many British Women Are Being Diagnosed With ADHD in Their 30s and 40s, and What It Means for Wellbeing

    Why So Many British Women Are Being Diagnosed With ADHD in Their 30s and 40s, and What It Means for Wellbeing

    Something shifted quietly over the past few years. Women in their 30s and 40s, many of them high-functioning, professionally capable, long-time over-achievers, started receiving a diagnosis that had never once been suggested to them in childhood: ADHD. For a lot of these women, the moment of diagnosis felt less like a revelation and more like a long-overdue explanation. A lifetime of exhaustion suddenly made sense. I’ve spoken to several women who described it as “finally being handed the manual to my own brain.”

    The numbers back this up. NHS Digital data shows that ADHD referrals across England have more than doubled in recent years, and women are driving a significant part of that rise. So why now? And what does a late diagnosis actually mean for your health and day-to-day life?

    Woman at desk reflecting — illustrating the experience of undiagnosed ADHD in adult women in the UK
    Photo by https://kaboompics.com/ on Pexels

    Why ADHD in women went unrecognised for so long

    The short answer is that ADHD research was built almost entirely around young boys. The hyperactive, disruptive child bouncing off classroom walls became the cultural template for what ADHD looked like, and clinicians used that template for decades. Girls who didn’t fit it were simply overlooked.

    ADHD in women and girls tends to present differently. Rather than overt hyperactivity, it often shows up as inattentiveness, emotional dysregulation, chronic disorganisation, and an exhausting inner mental chatter that never quiets down. Girls are also more likely to develop what researchers call “masking”, unconsciously mimicking neurotypical behaviour to fit in. That masking is effective enough to fool teachers, parents, and GPs. It is also, over decades, profoundly draining.

    By the time many women reach their 30s, the scaffolding they’ve built around their undiagnosed ADHD, rigid routines, over-reliance on lists, social withdrawal during stressful periods, starts to crack under the weight of adult responsibilities. Children arrive. Careers intensify. Relationships become more demanding. The coping strategies that worked at 22 stop working at 38. That’s often when the referral finally happens.

    The NHS diagnostic route vs going private

    If you’re seeking an ADHD assessment as an adult in the UK, you have two main options: the NHS or a private clinician. The reality of both routes is worth understanding clearly before you choose.

    Via the NHS, you’d typically start with your GP. If they agree a referral is appropriate, you’ll be added to a waiting list for an adult ADHD assessment, usually through a community mental health team or a specialist service. In many parts of England, those waiting lists currently run to two or three years. The NHS’s own guidance on adult ADHD diagnosis outlines what to expect from the assessment process, which typically includes a structured clinical interview, a review of childhood history (often involving a parent or someone who knew you as a child), and questionnaire-based rating scales.

    The private route cuts waiting times dramatically, assessments can sometimes be arranged within a few weeks, but costs vary considerably. A full private ADHD assessment in the UK typically costs between £500 and £1,500 depending on the provider and location. You can then ask your GP to take over prescribing under a “shared care agreement”, though not all GP practices agree to this, which has become a source of significant frustration for many women who’ve gone private.

    What the assessment actually involves

    A proper ADHD assessment for adults is not a single test. There’s no brain scan, no blood draw. It’s a clinical process that pulls together self-reported symptoms, behavioural history, and sometimes input from a partner or family member who can corroborate patterns they’ve observed.

    For women specifically, a good clinician will account for the fact that ADHD symptoms in women often don’t mirror the textbook male presentation. Hormonal fluctuations play a real role too: many women notice their ADHD symptoms worsen significantly in the week before their period, or during perimenopause, as oestrogen levels drop and dopamine regulation becomes harder. This hormonal dimension is something the medical community is only just beginning to take seriously.

    The assessment usually takes two to three hours in total, sometimes spread across multiple appointments. You’ll be asked about your childhood in detail, school reports, friendships, how you managed homework, whether you were described as “scatty” or “a daydreamer”. For women who masked effectively, this part can be surprisingly emotional. Recognising, retrospectively, that your struggles were not character flaws is not a small thing.

    Life after diagnosis: the wellbeing picture

    A diagnosis changes things, though not always in the ways you might expect. For many women, the initial response is grief, for the years spent struggling without support, for the self-blame, for the relationships and opportunities that might have gone differently. That grief is legitimate and worth sitting with rather than rushing past.

    Practically speaking, post-diagnosis support can include medication (stimulant medications like methylphenidate or lisdexamfetamine, or non-stimulants for those who can’t tolerate stimulants), ADHD-specific coaching, and cognitive behavioural therapy adapted for ADHD. Not everyone chooses medication, and that’s a valid position, but for many women, the right prescription significantly reduces the cognitive load they’ve been carrying silently for years.

    Sleep is often a major area of improvement. ADHD and poor sleep are tightly linked; the racing mind that makes it hard to wind down at night is a core feature of many women’s experience, not a separate problem. If that resonates, it’s worth reading about why so many British adults are going to bed later than their bodies want, the circadian dimension overlaps meaningfully with ADHD symptom patterns.

    Emotional regulation tends to improve too. The dysregulation that shows up as rejection-sensitive dysphoria, that intense, outsized emotional response to perceived criticism, is one of the most debilitating features of adult ADHD in women, and one of the least talked about. Having a framework for it changes how you relate to yourself during those moments.

    The lifestyle side of managing ADHD as an adult woman

    Medication is only part of the picture. Women post-diagnosis often find that the lifestyle factors they’d been told were “just good habits” turn out to be functional necessities for their particular neurology. Regular exercise, consistent sleep timing, and stable blood sugar all have a measurable impact on dopamine regulation, which is, at its core, what ADHD is about.

    The relationship between exercise and ADHD symptoms is genuinely compelling. Aerobic activity raises dopamine and norepinephrine levels in a way that partially mimics the effect of stimulant medication. I’d argue this is one area where the evidence is strong enough to treat exercise less like a nice-to-have and more like a prescription. Zone 2 cardio in particular, low-intensity, steady-state movement, is manageable even on high-symptom days when motivation is scarce.

    Gut health is another area worth paying attention to. The gut-brain axis affects neurotransmitter production in ways that are increasingly well understood, and women with ADHD often report that periods of dietary instability worsen their focus and mood significantly. There’s a useful overlap here with what we know about how repetitive meals can actually support gut stability, which may be more relevant for ADHD brains than previously appreciated.

    For women who are also navigating perimenopause alongside an ADHD diagnosis, the picture can feel complicated. Oestrogen’s role in dopamine regulation means that the hormonal changes of midlife can amplify ADHD symptoms considerably. Knowing that is genuinely useful, it means the right response isn’t always to push harder through the fog, but to adjust expectations and support accordingly. If your nervous system feels overwhelmed more often than it used to, it might be worth reading about the signs that your nervous system is dysregulated, the overlap with ADHD is significant.

    What to do if you think this might apply to you

    Start with your GP. Go in with specifics: how long you’ve experienced these difficulties, what impact they have on work and relationships, whether they’ve been lifelong or changed over time. Ask explicitly about an adult ADHD assessment. If the waiting list is long and you have the means to go private, research providers carefully, look for clinicians who are registered with the British Psychological Society or are on the GMC register, and check whether your GP is likely to accept a shared care arrangement for prescribing.

    A diagnosis at 35 or 45 is not a second-best outcome. For many women, it’s the thing that finally makes the other work, the therapy, the habits, the self-compassion, actually land.

    Frequently Asked Questions

    Why are so many women getting an ADHD diagnosis later in life in the UK?

    Historically, ADHD research focused on boys, so the quieter, more internalised presentation common in girls was regularly missed or misattributed to anxiety or low confidence. Many women only seek assessment when coping strategies built up over decades begin to fail under the pressure of adult life, often in their 30s or 40s.

    How do I get an ADHD assessment as an adult woman on the NHS?

    Speak to your GP and ask for a referral to an adult ADHD service. The GP will typically conduct a brief initial review before referring you. NHS waiting times across England currently run to two or three years in many areas, so some women choose to self-fund a private assessment in the meantime.

    How much does a private ADHD assessment cost in the UK?

    Private adult ADHD assessments in the UK typically cost between £500 and £1,500 depending on the provider, location, and whether the assessment spans multiple appointments. After a private diagnosis, you can ask your GP to take over prescribing on an NHS shared care basis, though not all practices agree to this.

  • Why Eating the Same Meals on Repeat Might Be Better for Your Gut Than You Think

    Why Eating the Same Meals on Repeat Might Be Better for Your Gut Than You Think

    The received wisdom has been pretty consistent for a few years now: eat more variety, rotate your proteins, try a new vegetable every week, and your gut microbiome will thank you. It is solid advice, broadly speaking. But there is a quieter body of research building that complicates the picture, and I think it deserves more attention than it gets. Because a significant number of people in the UK do not eat a wildly varied diet. They eat roughly the same ten to fifteen meals on rotation, and they feel fine. The question is whether that consistency is actually harming their gut health, or whether the relationship between dietary routine and the microbiome is more nuanced than the “eat the rainbow” crowd suggests.

    Meal prep containers on a kitchen counter, representing eating same meals for gut health in the UK
    Photo by Nataliya Vaitkevich on Pexels

    What the research on dietary consistency actually shows

    The gut microbiome is a community of trillions of bacteria, fungi, and other microorganisms living in your digestive tract. A stable, resilient microbiome is generally associated with better immunity, mood regulation, and metabolic health. The diversity argument goes that more varied food = more varied bacterial strains = better outcomes. And there is real evidence for that.

    But stability is not the same thing as stagnation. Research published in Cell Host and Microbe found that microbiome composition fluctuates considerably day to day, and that some of that fluctuation is driven by inconsistent eating patterns rather than dietary variety per se. A consistent dietary pattern, even a relatively simple one, can produce a stable microbial environment, which may actually be preferable to a chaotic one that swings between high-fibre weeks and takeaway-heavy weekends.

    A 2021 study from King’s College London, which used data from the ZOE personalised nutrition project, found that individual microbiome responses to food vary enormously. Two people eating identical diets can have dramatically different microbial outcomes. That finding cuts both ways: it means variety alone is not a guarantee of a healthy gut, and it means consistency alone is not a guarantee of a damaged one.

    Why routine might actually help rather than harm

    Think of your gut bacteria as a workforce. They adapt to the raw materials they receive regularly. When you eat broadly the same meals week in, week out, the bacteria that thrive on those particular substrates become well-established. They colonise effectively, they reproduce efficiently, and they get good at extracting what your body needs from those specific foods.

    Introduce a sudden and dramatic dietary shift and you can temporarily destabilise that community. Anyone who has gone from a fairly plain diet to a week of holiday food and experienced digestive discomfort will recognise this. The microbiome can adapt, but it takes time, roughly two to four weeks for meaningful shifts in composition. Short-term variety may produce short-term disruption without long-term gain.

    This does not mean eating the same meals is universally fine regardless of what those meals are. The quality and fibre content of your routine still matters enormously. A consistent diet of plain grilled chicken and white rice is very different from a consistent diet that includes legumes, wholegrains, fermented foods, and a couple of different vegetables even if those vegetables are always the same ones.

    What this means for busy UK adults who rely on meal routines

    Most people I speak to about their eating habits describe something closer to a rotation than a varied menu. Monday tends to be pasta. Tuesday might be stir-fry. Friday is usually a takeaway. There is genuine comfort and practicality in that, and the data increasingly suggests there is also no need to feel guilty about it, provided those repeating meals carry adequate fibre and a reasonable spread of nutrients.

    The practical framing, then, is this: if you rely on a meal routine, optimise the meals in that routine rather than overhauling it entirely. A few tweaks can make a significant difference to how well that routine supports your gut microbiome.

    • Swap white pasta or rice for wholegrain versions in your regular meals. You are still eating the same dishes, but the fibre profile changes substantially.
    • Add a fermented food to your weekly shop and make it part of the routine. A spoonful of live yoghurt, a portion of kimchi with your stir-fry, or some kefir in the morning costs very little and introduces beneficial bacterial strains consistently.
    • Rotate just one element of a regular meal. If you always make a grain bowl, keep the base the same but alternate between chickpeas, lentils, and black beans. That small swap meaningfully diversifies your prebiotic fibre without disrupting the routine.

    This kind of micro-variety within a stable structure is, I’d argue, a more realistic goal for most British adults than dramatically reinventing the weekly shop every fortnight.

    The fibre question is still the most important one

    Regardless of whether you eat the same meals or a different one every night, the single biggest driver of microbiome health in the existing evidence base is fibre intake. The NHS recommends 30g of dietary fibre per day for adults, yet the average UK adult consumes closer to 18g, according to the British Dietetic Association. That gap matters far more than the variety debate.

    If your meal rotation happens to include oats at breakfast, a sandwich on wholegrain bread at lunch, and a dinner with vegetables and legumes, you may be doing better than someone who eats a wide variety of low-fibre processed foods. The baseline of your diet matters. And if you are curious about how your gut connects to other aspects of your health, the gut-brain connection is real, with researchers now linking microbiome composition to mood, social behaviour, and even how we respond to stress.

    There is also something worth saying about the psychological dimension of eating. For people who struggle with food anxiety, disordered eating patterns, or simply the cognitive load of planning varied meals, a consistent routine can reduce stress significantly. Lower stress means lower cortisol. Lower cortisol is associated with better gut motility and a more stable microbiome. The indirect benefits of a routine are not nothing.

    When sameness becomes a problem

    There are situations where a very narrow eating routine does cause issues. If your rotation excludes entire food groups, particularly plant foods, or relies heavily on ultra-processed options, then the microbial consequences are likely negative. Research consistently links ultra-processed food consumption with reduced microbiome diversity, regardless of whether it is eaten routinely or occasionally.

    Similarly, if you notice persistent digestive symptoms, fatigue, or skin flare-ups that correlate with your current eating pattern, that is worth paying attention to. A GP or registered dietitian can help distinguish between a microbiome that needs support and symptoms caused by something else entirely. The way nutrients interact with your body is more individual than most people realise, and a single dietary template does not suit everyone.

    The point is not that variety is bad. Broader dietary variety, particularly of plant foods, remains a sensible long-term goal. But the idea that eating the same meals week after week is inherently damaging to your gut health does not hold up well under scrutiny. If your routine is built on reasonably whole, fibre-containing foods, your microbiome is likely more stable than stressed. And for most people, stability is exactly what they are after. Start from your baseline, make it a good one, and the rest tends to follow.

    Frequently Asked Questions

    Is eating the same meals every day bad for your gut health?

    Not necessarily. Research suggests microbiome stability can come from consistent dietary patterns, provided those meals are built around fibre-rich, whole foods. The quality of your routine matters more than its variety alone.

    How much dietary variety do I actually need for a healthy gut microbiome?

    There is no fixed number, but diversifying within your existing routine, such as rotating legumes or adding a fermented food, can meaningfully improve microbiome diversity without overhauling your entire weekly menu. The NHS recommends 30g of fibre daily as a core target.

    Can a consistent diet cause microbiome problems over time?

    It can if that diet is low in fibre or heavy in ultra-processed foods. A narrow routine lacking plant diversity will limit the range of bacterial strains your gut can sustain. Adding even small amounts of varied plant-based fibre to a regular rotation helps.

    What are the best foods to include in a gut-friendly meal rotation?

    Wholegrains, legumes (lentils, chickpeas, beans), vegetables, and fermented foods like live yoghurt, kefir, or sauerkraut are well-supported by the evidence. Including a few of these consistently in your routine is more effective than occasional “superfoods” weeks.

    Should I see a doctor if I have digestive symptoms despite eating a consistent diet?

    Yes, if symptoms are persistent. Ongoing bloating, irregular bowel habits, or fatigue linked to eating warrant a GP conversation. They may refer you to a registered dietitian or investigate conditions like irritable bowel syndrome (IBS), which affects around 10-20% of UK adults.

  • Training Fasted vs Fed: What the Evidence Actually Says for Morning Exercisers in the UK

    Training Fasted vs Fed: What the Evidence Actually Says for Morning Exercisers in the UK

    The debate has been running for years. Train before breakfast and your body burns more fat. No, eat first or you’ll lose muscle. Take creatine. Don’t take creatine fasted. The noise is relentless, and if you’re trying to work out in the window between your alarm and a packed commute into work, it can feel impossible to know what to actually do. I’ve sifted through the research so you don’t have to, and the honest answer is more nuanced, and more practical, than most fitness content admits.

    Man running fasted in a morning park, illustrating fasted training evidence UK
    Photo by Pexels LATAM on Pexels

    What fasted training actually means

    When people say “fasted training”, they generally mean exercising after an overnight fast of roughly eight to twelve hours, before consuming any calories. For most people in the UK, that means rolling out of bed and heading straight to the gym, park, or living room without breakfast. It does not mean a multi-day fast or anything remotely extreme. Physiologically, being in a fasted state means lower insulin levels and, in theory, a greater reliance on stored fat as fuel. That part is real. The question is whether it translates into meaningfully better outcomes.

    What the research actually shows on fat loss

    The fasted training evidence UK fitness communities often cite goes back to a frequently referenced 2016 study published in the British Journal of Nutrition, which found that men who ran fasted burned up to 20% more fat during the session compared to those who had eaten beforehand. That sounds compelling. But here is the catch: fat oxidation during a workout does not automatically equal greater fat loss over 24 hours. The body is good at compensating. If you burn more fat during your run, you tend to burn more carbohydrate later in the day when you eat, and vice versa. Total fat loss over time depends far more heavily on your overall calorie balance than on the timing of any single session.

    A review published in the Journal of the International Society of Sports Nutrition looked at multiple studies comparing fasted and fed aerobic exercise and concluded there was no significant difference in body composition outcomes when total calories were matched. So if you eat exactly the same amount either way, your body fat over weeks and months is unlikely to differ based on breakfast timing alone. That does not mean fasted training is useless. It means the mechanism is different from what most people assume.

    The muscle retention question

    This is where fasted cardio becomes more complicated, especially for anyone doing strength training. Lifting weights in a fasted state does raise cortisol and can increase muscle protein breakdown to some degree, particularly in longer or more intense sessions. For a 20-minute morning jog, this is barely relevant. For a 60-minute heavy lifting session, it is worth thinking about.

    Protein timing research suggests that having amino acids available around your training session, before or after, helps with muscle protein synthesis. If you’re training fasted and then not eating for another two hours because your commute is awkward, you’re extending the window in which your muscles are essentially waiting for raw materials. I’d argue this matters more if building or preserving muscle is your primary goal than if you’re just going for a steady-state morning run.

    This connects neatly to what happens to your body at a desk all day, if your morning workout is one of the few genuine movement windows you have, getting the most out of it matters, and arriving at work having had nothing but coffee is not always the best set-up for that.

    How UK breakfast habits and commuting complicate things

    The practical reality of morning training in Britain is that a lot of people are working around a 6–8am session, a train or drive into a city centre, and either a full day of work or childcare commitments starting before 9am. That schedule does not always leave time for a proper pre-workout meal, a 45-minute digestion window, and a cool-down. Which is exactly why fasted training is popular here, it removes a variable, not because it is metabolically superior.

    According to data from the British Nutrition Foundation, around a third of UK adults regularly skip breakfast. For that group, training fasted is not a deliberate biohacking choice; it is just what happens. If you are in that camp, the evidence suggests you are not sabotaging yourself. You are just training fasted, which is fine for most moderate-intensity sessions.

    Where it gets interesting is the performance side. Most research consistently shows that having carbohydrates before exercise improves high-intensity performance. If your morning session involves sprints, heavy compound lifts, or anything requiring genuine top-end output, eating something beforehand, even something small like a banana or a small bowl of oats, will likely help you perform better. Better performance in a session usually means a better training stimulus, which over time drives better results. That chain of logic is worth respecting.

    A practical framework depending on your goal

    Rather than picking a side, I think the smarter approach is to match your strategy to what you are actually trying to achieve. If fat loss is the goal and your session is steady-state cardio lasting under 45 minutes, training fasted is completely reasonable and the evidence does not show you’re leaving meaningful results on the table. If your goal is building muscle or maintaining it during a calorie deficit, having some protein before or immediately after, a Greek yoghurt, a protein shake, eggs if you have time, is worth the effort. And if your session involves anything genuinely intense, eating something beforehand is likely to produce better output and, over time, better adaptation.

    It is also worth acknowledging that sleep quality affects how you feel training fasted. If you are regularly going to bed late and disrupting your hormones, training fasted on poor sleep can feel disproportionately hard, and it can blunt motivation over time. The fasted vs fed decision does not exist in isolation from your overall recovery picture.

    What about supplements taken fasted?

    A common question is whether to take supplements like creatine or magnesium before a fasted session. Creatine does not require food to be absorbed, you can take it at any time and it saturates muscle tissue over days, not hours. Magnesium is worth being careful with on an empty stomach, as some forms can cause digestive discomfort without food present. Caffeine, the most widely used pre-workout aid in the UK, works fine fasted and may actually enhance fat oxidation during exercise slightly, though as discussed, that does not automatically translate into greater fat loss overall.

    The bottom line on fasted training

    Fasted training is not a magic protocol and it is not the mistake some gym voices make it out to be. The fasted training evidence UK research collectively points to is this: for fat loss over time, it makes little difference if your diet is consistent. For performance and muscle retention, eating something, particularly protein, is worth it if your session is long or intense. Your commute, your sleep, and your overall weekly calorie intake matter considerably more than whether you had toast before a 30-minute jog.

    The NHS recommends adults do at least 150 minutes of moderate-intensity activity per week. How you fuel that activity should fit your life, not someone else’s optimised protocol. Pick the approach you can sustain, and the results will follow. You can read more about exercise recommendations on the NHS physical activity guidelines for adults.

    Frequently Asked Questions

    Is it better to exercise on an empty stomach in the morning?

    For moderate-intensity cardio lasting under 45 minutes, fasted exercise is perfectly fine and current research shows no meaningful difference in fat loss compared to exercising fed. For high-intensity or strength sessions, having something small beforehand tends to improve performance and muscle retention.

    Does fasted cardio burn more fat?

    You do oxidise more fat during a fasted session, but the body compensates across the rest of the day. Multiple studies show no significant difference in total body fat loss over time between fasted and fed training when total calorie intake is the same.

    Will I lose muscle if I train fasted?

    Short, moderate-intensity fasted sessions are unlikely to cause meaningful muscle loss in most people. Longer or heavier sessions fasted can increase muscle protein breakdown slightly, so having protein either before or shortly after training is advisable if muscle preservation is a priority.

    What should I eat before an early morning workout in the UK?

    Something easily digestible and quick to prepare: a banana, a small pot of Greek yoghurt, a slice of toast with peanut butter, or a protein shake all work well and can be consumed 20 to 30 minutes before training if time is short.

    Can I drink coffee before fasted training?

    Yes. Black coffee does not break a fast in any meaningful physiological sense and may slightly enhance fat oxidation during exercise. It also improves alertness and performance, making it one of the more useful tools for early morning sessions.

  • Why British Adults Are Going to Bed Later Than Ever, and What It’s Doing to Your Hormones

    Something has shifted in the way British people end their evenings. According to ONS time-use data, adults in the UK are, on average, going to bed around 40 minutes later than their counterparts did two decades ago. Forty minutes sounds trivial. It isn’t. When that drift happens night after night, and when it compounds across a population that is simultaneously more screen-saturated and more stressed than any previous generation, the effects on late bedtimes circadian rhythm disruption become genuinely significant. I’ve been looking at this data for a while now, and the picture it paints is not comfortable reading.

    What the data actually shows about British bedtimes

    The ONS time-use surveys are dry documents, but buried inside them is a clear trend: the midnight hour is no longer the preserve of shift workers and teenagers. A substantial proportion of working-age adults in England and Wales are now regularly in bed after midnight on weekday nights, and considerably later at weekends. Sleep researchers at the University of Surrey have separately found that social jetlag, the gap between your body clock’s preferred sleep time and your actual sleep time, is widening in the UK population. For many people, that gap is now over an hour. Some reports put it closer to 90 minutes for those aged 18 to 35.

    The causes are not mysterious. Streaming platforms design their interfaces specifically to prevent natural stopping points. Smartphone use after 10pm has become the norm rather than the exception. And crucially, the boundary between work and home has blurred so thoroughly that many people spend the first part of their evening finishing tasks they couldn’t complete during the working day. The evening that used to wind down now winds up before it winds down.

    What late bedtimes actually do to your circadian rhythm

    Your circadian rhythm is not a vague concept. It is a precise biological clock, regulated primarily by light and temperature, that times the release of almost every hormone in your body. Melatonin, cortisol, insulin, leptin, ghrelin, all of them operate on a schedule. When you consistently push your bedtime later, you are not simply resting later; you are shifting the entire hormonal architecture of your body relative to the light-dark cycle outside your window.

    Cortisol is supposed to peak early in the morning, pulling you awake and alert. In people with chronic late bedtimes, that peak often arrives when they are still asleep, which means they either sleep through the cue or wake feeling groggy and unrefreshed despite technically getting enough hours. Melatonin, meanwhile, may not reach adequate concentrations until well past the point where light exposure has started again, creating a situation where the body is physiologically night-time whilst the world is already in daylight. This is not a marginal inconvenience. It is a mismatch between your internal biology and your external environment, and sustained over months or years it has measurable consequences.

    The metabolic and hormonal consequences

    Late bedtimes circadian rhythm disruption has a particularly pronounced effect on metabolic health. Studies published in journals including The Lancet Diabetes & Endocrinology have found that people who sleep late relative to their chronotype, meaning they sleep later than their biology prefers, show higher levels of insulin resistance, elevated fasting glucose, and a tendency to consume more calories in the evening when the gut is least prepared to process them efficiently. The gut has its own circadian clock, and it is calibrated for lighter meals as evening progresses, not a full dinner at 10pm.

    Leptin and ghrelin, the hormones that govern hunger and satiety, are also timed around the circadian cycle. Push sleep late and you push the window of elevated ghrelin later too, meaning late-night hunger becomes a biological reality rather than a lack of willpower. I’d argue this alone explains a significant proportion of the late-evening snacking behaviour that many people assume is simply a bad habit. It is, in part, a hormonal signal that has been misaligned by a late schedule.

    For women specifically, the interplay with reproductive hormones adds another layer of complexity. Oestrogen and progesterone are both sensitive to sleep quality and timing. Disrupted circadian rhythms have been linked in several cohort studies to irregular cycles, worsened premenstrual symptoms, and more difficult perimenopause transitions. If you are already thinking about how much of your daily routine is quietly working against your body, late sleep timing deserves to be on that list.

    Why this matters more than total sleep hours

    Public health messaging around sleep has focused almost entirely on duration, the NHS recommends 7 to 9 hours for adults, and that guidance is sound. But duration is only half the picture. The timing of sleep relative to the natural light cycle matters enormously, and this is the part that rarely gets discussed. You can sleep eight hours starting at 2am and still experience measurable circadian disruption, elevated cortisol irregularity, and impaired glucose metabolism the following day. Whereas seven hours starting at 10:30pm, for many people, produces genuinely better hormonal outcomes.

    This doesn’t mean everyone needs to be in bed by ten. Chronotype, your genetically influenced preference for earlier or later sleep, is real, and forcing a committed evening person onto a lark’s schedule creates its own problems. The key is reducing the gap between your biological sleep preference and your actual bedtime. Even a 30-minute shift earlier, sustained consistently, has been shown in sleep research to improve morning cortisol rhythm, reduce social jetlag, and improve next-day mood and cognitive performance.

    Small timing adjustments that make a measurable difference

    I’ve tried most of these myself, and the ones that actually moved the needle were simpler than I expected. The single most effective change is shifting the first bright light exposure of the morning earlier, opening the curtains immediately upon waking, or stepping outside briefly within the first 20 minutes of rising. This anchors your circadian clock to the natural light cycle and, over several days, begins to pull your biological evening earlier too. Morning light is the most powerful circadian signal your body receives.

    Dimming artificial light after 9pm has a compounding effect. This does not require smart bulbs or special equipment; simply moving to a lamp rather than overhead lighting, and reducing screen brightness, is enough to reduce the melatonin-suppressing effect of blue-spectrum light in the evening. Pair that with a consistent wake time, even at weekends, or at least within an hour of your weekday time, and the circadian anchor strengthens noticeably within a fortnight.

    Meal timing also feeds back into circadian regulation more than most people realise. Finishing your evening meal by 7:30 or 8pm, rather than at 9:30 or later, reduces the metabolic load on your gut during the hours it is biologically winding down. This is not intermittent fasting dressed up in new language; it is simply working with the timing signals your body already uses.

    For anyone managing a health blog, a wellness business, or any kind of digital presence alongside these routines, late evenings often get consumed by admin tasks that feel urgent. Even the choice of basic infrastructure can compound evening stress, switching to reliable WordPress hosting for small businesses is the kind of friction-reducing decision that genuinely frees up evening time rather than burning it on technical problems. Small environment changes stack.

    The relationship between reward-seeking habits and late evenings is also worth acknowledging honestly. A lot of late-night screen use isn’t passive; it is the brain chasing stimulation after a day that felt unrewarding or unfinished. Addressing that at its source, finding genuine rest and satisfaction earlier in the evening, tends to be more durable than simply setting a phone alarm to go to bed.

    The broader point is this: late bedtimes circadian rhythm disruption is not a minor inconvenience that a weekend lie-in can repair. The biological debt accumulates slowly and quietly, showing up first as mood instability and cravings, then as metabolic shifts, and eventually in longer-term hormonal patterns that are much harder to reverse. The good news is that the circadian system is responsive. You do not need a radical overhaul. You need consistent, modest shifts, and you need to start them before you feel the need to.

    Frequently Asked Questions

    How late is too late to go to bed for your health?

    There is no single universal threshold, because chronotype varies between individuals. However, sleep researchers generally find that consistently sleeping after 1am, even for a full seven or eight hours, is associated with greater circadian disruption, higher social jetlag, and measurable metabolic effects compared to sleeping at or before midnight. The key metric is the gap between your biological sleep preference and your actual bedtime, not the hour on the clock alone.

    Can going to bed later really affect your hormones?

    Yes, and quite directly. Cortisol, melatonin, insulin, leptin, and ghrelin all follow circadian schedules. Chronic late bedtimes shift the timing of these hormones relative to the external light-dark cycle, which can impair morning alertness, increase evening hunger, reduce insulin sensitivity, and disrupt reproductive hormone patterns in women. These are not subtle effects; they show up in blood markers and are well documented in peer-reviewed research.

    Does sleeping in at weekends cancel out late weekday bedtimes?

    Partly, but not fully. Weekend lie-ins can partially offset some sleep debt, but they also widen social jetlag, the mismatch between your biological clock and social schedule, which itself carries metabolic and mood consequences. Sleep researchers recommend keeping weekend wake times within an hour of weekday times to maintain a stable circadian anchor rather than repeatedly shifting it.

    What is social jetlag and how does it affect UK adults?

    Social jetlag refers to the difference between when your body clock wants to sleep and wake versus when your social and work schedule forces you to. UK research, including work from the University of Surrey’s Sleep Research Centre, has found that a significant proportion of British adults have a social jetlag of over an hour. It is associated with higher rates of obesity, low mood, and cardiovascular risk markers, independent of total sleep duration.

  • Noise Pollution and Your Health: What Living Near a UK Road or Railway Is Doing to Your Body

    Most people assume that once you get used to the noise, it stops bothering you. The traffic rumble at 2am, the freight train at 5am, the bass-heavy lorry that shakes the window frame. You habituate. You cope. And after a while, you barely notice it consciously. The problem is that your body never stops noticing. Research published in the European Heart Journal found that road traffic noise is independently associated with higher rates of cardiovascular disease, even when other risk factors are controlled for. The noise doesn’t have to wake you up to harm you. That’s what makes the noise pollution health effects UK residents face so easy to underestimate.

    How chronic noise disrupts sleep, even when you can’t feel it

    The body doesn’t fully switch off during sleep. Your auditory system stays alert, and when it detects a sudden or sustained noise above roughly 30 decibels, it can trigger a stress response. Cortisol levels rise. Heart rate increases. Sleep stages fragment. You may not fully wake up, but you slip from deeper, restorative sleep into lighter stages far more frequently than your brain needs.

    The World Health Organisation recommends that outdoor noise at night should not exceed 40 decibels for good sleep health. UK road traffic regularly exceeds this. A busy A-road at night can sit at 55 to 65 decibels. Railway lines, depending on frequency of use, can spike higher. And because many UK homes, particularly older terraced housing and Victorian flats, have single-glazed windows or limited wall insulation, that outdoor noise becomes indoor noise almost without reduction.

    The knock-on effects compound quickly. Fragmented sleep means less slow-wave sleep, which is where physical repair, immune regulation, and memory consolidation happen. Over months and years, the cumulative deficit adds up to something much harder to reverse than a single bad night.

    The cardiovascular link is stronger than most people realise

    The UK government’s own review of environmental noise and health acknowledges a link between long-term noise exposure and increased risk of ischaemic heart disease, hypertension, and stroke. The proposed mechanism is partly sleep-related and partly direct: noise activates the sympathetic nervous system, which raises blood pressure and increases inflammatory markers, even during waking hours.

    For people who already carry cardiovascular risk, whether through family history, diet, weight, or existing conditions, living with chronic noise likely amplifies that risk. This isn’t alarmist. It’s physiology. The body interprets persistent environmental threat as a reason to stay in low-level fight-or-flight mode, and that state has a cost.

    There’s also emerging evidence around atrial fibrillation. A large Danish study tracking over 3.6 million people found that for every 10-decibel increase in road traffic noise, the risk of atrial fibrillation rose by 8%. The UK’s traffic density, especially around major urban arterials in London, Manchester, Birmingham, and Leeds, makes this relevant to a large portion of the population.

    Mental health: the slower, quieter toll

    Noise affects mood in ways that are harder to trace than a sleep chart or a blood pressure reading. Living in a persistently loud environment increases psychological stress, even background stress you might not label as anxiety. Over time, this contributes to elevated rates of depression, generalised anxiety, and cognitive fatigue.

    The mechanism overlaps with what we know about cortisol. Chronic low-level stress keeps cortisol slightly elevated throughout the day, which gradually disrupts serotonin and dopamine regulation. If you’ve read our piece on reward-seeking habits and the brain, you’ll recognise the pattern: a dysregulated stress system tends to push people towards fast dopamine hits, scrolling, snacking, alcohol, as coping mechanisms. Noise may be one of the upstream causes that nobody accounts for.

    Children are particularly vulnerable. Studies from schools near major airports in the UK have shown measurable impacts on reading comprehension and working memory in children exposed to persistent noise. The same mechanisms are plausible in adults who work from home in noisy environments, which is now a significant portion of the working population.

    UK urban density makes this worse than most people assume

    The UK has some of the highest urban density in Europe, particularly in England. Around 84% of the English population lives in urban areas, and a large proportion of that housing stock was built before any noise considerations were factored into planning. Victorian terraces backing onto railways, Edwardian semis on arterial roads, post-war flats above main roads, these aren’t edge cases. They’re the reality of how millions of people in the UK live.

    The situation is slowly improving for new-build properties, which now face stricter acoustic standards under building regulations. But renters in older stock have limited options, and many homeowners simply cannot afford the upgrades that would make a real difference. This creates a health inequality dimension too: noisier housing is typically cheaper, which means lower-income households bear a disproportionate share of the noise pollution health effects UK-wide.

    What you can actually do about it

    You can’t move the road. But there are practical steps that genuinely help, both for renters and homeowners.

    Secondary glazing is one of the most cost-effective interventions for noise reduction. Unlike full window replacement, secondary glazing adds an inner layer to an existing frame and can reduce traffic noise by 40 to 45 decibels. It’s also reversible, which makes it viable for renters with landlord permission.

    Heavy curtains and draught excluders don’t match glazing for noise reduction, but they do help at the margins. Any gap is a noise channel, sealing door frames, letterboxes, and window edges reduces how much sound enters at night.

    White noise or pink noise doesn’t reduce noise, but it can mask it effectively enough to reduce sleep fragmentation. The NHS Sleep Service acknowledges background sound as a useful tool for people whose sleep is disturbed by environmental factors. There’s a meaningful difference between passively suffering a lorry at 3am and choosing a consistent auditory background your brain can filter out.

    Sleep positioning matters too. If noise primarily enters from a street-facing window, sleeping in the deepest part of the room reduces exposure. Simple, but underused.

    For homeowners with some budget, acoustic panels, roof insulation, and solid-core internal doors all contribute. None of these are cheap, but they’re cheaper than the long-term health cost of chronic poor sleep, and they add value to the property.

    If you’ve been waking frequently and struggling to understand why, it’s worth reading about what cumulative physical stressors do to the body over time. Noise is one of the most overlooked on that list.

    When to take the noise concern further

    If you’re experiencing symptoms you suspect are noise-related, persistent fatigue, frequent night waking, anxiety, elevated resting blood pressure, it’s worth raising with your GP. They can refer you for a sleep assessment and consider whether your environment is a contributing factor to cardiovascular or mental health symptoms.

    Local councils also have a statutory duty to address noise nuisance. If your noise is coming from a specific identifiable source (a commercial premises, a nightclub, industrial equipment) rather than general traffic, the Environmental Health team at your local council can investigate. Persistent sleep disruption related to stress and a constantly activated nervous system follows a recognisable pattern, one that’s also described in our article on what chronic stress does to the body’s systems over time.

    Noise isn’t going away from UK cities. But understanding what it’s doing below the level of conscious awareness is the first step to actually managing its impact on your health.

    Frequently Asked Questions

    How loud does noise need to be to affect your health?

    The World Health Organisation sets a nighttime outdoor noise guideline of 40 decibels for sleep health. Many UK roads regularly exceed 55 to 65 decibels at night, which is enough to cause physiological stress responses and sleep fragmentation even without fully waking you. Daytime exposure above 65 decibels is also associated with elevated blood pressure over time.

    Does noise pollution really affect heart health?

    Yes. The UK government’s own review of environmental noise acknowledges a link between long-term traffic noise exposure and higher rates of ischaemic heart disease, hypertension, and stroke. The mechanism involves chronic activation of the sympathetic nervous system, which raises blood pressure and inflammation markers even during waking hours.

    What is the cheapest way for renters to reduce noise at home?

    Secondary glazing is one of the most effective options and is reversible, making it suitable for renters with landlord permission. Heavy curtains, sealing gaps around windows and doors, and using white or pink noise at night are lower-cost steps that can also reduce the impact of traffic and railway noise on sleep quality.

    Can noise exposure cause anxiety and depression?

    Chronic environmental noise keeps the stress system in a low-level activated state, which over time can disrupt serotonin and dopamine regulation. Research links long-term noise exposure to higher rates of anxiety, depression, and cognitive fatigue, particularly in people living near busy roads, railways, or airports.

  • Postural Hypotension: Why You Feel Dizzy When You Stand Up and When to Mention It to Your GP

    Postural Hypotension: Why You Feel Dizzy When You Stand Up and When to Mention It to Your GP

    You push yourself up from the sofa and for a second the room tilts. Your vision goes grey at the edges, your head swims, and you grab the nearest surface until it passes. Then, five seconds later, you’re fine. Most people file this away as something vaguely normal, barely worth mentioning. But that brief, unsettling moment has a name, a mechanism, and occasionally a clinical significance that makes it worth understanding properly.

    The technical term is postural hypotension, sometimes called orthostatic hypotension. It describes a sudden drop in blood pressure that happens when you move from lying or sitting to standing. Blood pools briefly in the lower body, the heart hasn’t quite compensated yet, and the brain notices the dip in supply. Result: that familiar head rush. Understanding the dizzy when standing up causes common in the UK can help you work out whether you’re looking at something trivial or something worth a conversation with your GP.

    Woman steadying herself on sofa after feeling dizzy when standing up, a common cause investigated in UK health settings

    What actually happens in your body

    When you stand, gravity pulls roughly half a litre of blood downward into your legs and abdomen almost immediately. A healthy cardiovascular system compensates within seconds: the heart rate nudges up, the blood vessels in the legs constrict, and blood pressure returns to normal. This whole process is managed by the autonomic nervous system, specifically the baroreceptors sitting in the walls of the aorta and carotid arteries. They sense the pressure drop and signal the heart to correct it.

    When that chain of events is sluggish or partially broken, blood pressure stays low for a beat too long. The brain, sensitive to even small reductions in oxygen delivery, produces lightheadedness, blurred vision, or that peculiar grey-out feeling. For most people most of the time, this is brief and benign. The question is why the compensation is delayed.

    The most common causes, starting with the obvious ones

    Dehydration is the single most frequent culprit. If your blood volume is low because you haven’t drunk enough water, the system has less to work with and the pressure drop on standing is more pronounced. This is especially common in warm weather, after exercise, or following a night of poor sleep where you’ve sweated without replenishing. According to NHS guidance on dehydration, most adults need around 1.5 to 2 litres of fluid daily under normal conditions, and many people in the UK habitually fall short.

    A prolonged period of bed rest or sitting for a long time has a similar effect. The body adapts to being horizontal and the compensatory reflexes get a little lazy. If you spend most of the day at a desk, this is worth bearing in mind: the physical effects of prolonged sitting go beyond back pain and include subtle changes to circulation that can make postural lightheadedness more likely.

    Large meals can also trigger it. Blood is redirected to the digestive system after eating, which reduces what’s available elsewhere. Standing quickly after a heavy meal is one of the more reliable ways to provoke the head rush.

    Medication side effects are a significant factor

    A long list of commonly prescribed medicines can worsen postural hypotension. Antihypertensives (drugs taken to lower blood pressure), diuretics (water tablets), alpha-blockers prescribed for prostate conditions, some antidepressants, and certain Parkinson’s medications are all known to reduce blood pressure in ways that exaggerate the standing response. If you started noticing dizziness on standing around the time a new prescription began, that correlation is worth flagging with your prescriber. Never stop or adjust medication without speaking to a clinician, but do mention it: sometimes a timing change or dose adjustment resolves the problem entirely.

    Alcohol is in the same category, temporarily dilating blood vessels and reducing the efficiency of the compensatory response. The morning after a night out is a classic time for pronounced dizziness on standing, partly for this reason and partly because alcohol is dehydrating.

    When the autonomic nervous system is the problem

    More persistent postural hypotension, where it happens regularly regardless of hydration or medication, sometimes points to autonomic dysfunction. The autonomic nervous system manages all the unconscious regulatory processes in the body, including blood pressure on movement. Conditions like diabetes (through peripheral neuropathy), Parkinson’s disease, and some autoimmune conditions can affect autonomic function over time. This type is less common but more clinically significant, which is why persistent symptoms warrant proper investigation rather than self-management alone.

    Age plays a role too. The baroreceptor reflex becomes less responsive with age, which is why postural hypotension is more common in people over 65. The British Heart Foundation estimates it affects around 20% of adults over 65 in the UK, and it’s one of the more common causes of falls in older people. If you have an older relative who has had an unexplained fall, dizziness on standing is something their GP should specifically ask about.

    How your resting cardiovascular health fits in

    Your baseline cardiovascular function matters here. A resting heart rate at the higher end of normal, or blood pressure that’s already sitting on the low side, means there’s less buffer when you stand. Understanding what your resting heart rate means is a useful starting point for getting a clearer picture of your cardiovascular baseline, because changes in both metrics are relevant to how your body handles postural changes.

    What you can do yourself

    For mild, occasional dizziness on standing, a few practical adjustments make a real difference. Stand up in stages rather than going from horizontal to fully upright in one movement. Sit on the edge of the bed or sofa for a few seconds first. Contract your leg muscles before you stand, which helps push blood back upward. Drink more water through the day rather than trying to compensate in one go. If you’re prescribed diuretics, check with your GP whether the timing could be shifted to reduce the effect during your most active hours.

    Compression socks or support stockings, often dismissed as something only for long-haul flights, are genuinely effective at reducing blood pooling in the legs and are sometimes recommended specifically for people with recurrent postural hypotension. They’re available from most pharmacies without a prescription.

    There’s also a broader lifestyle angle. Autonomic function is closely tied to overall nervous system health, and chronic stress, poor sleep, and a sedentary routine all affect how well the system regulates blood pressure under changing conditions. Addressing those foundations doesn’t just help with this specific symptom; it pays off across a lot of other areas too. Similarly, if you’re dealing with anxiety that seems to be affecting your physical symptoms, signs of nervous system dysregulation are worth reading up on, since the overlap with autonomic symptoms is real.

    When to speak to your GP

    Occasional lightheadedness on standing in an otherwise healthy adult is usually nothing serious. Speak to your GP if: it’s happening regularly (more than a few times a week); you’ve actually fainted rather than just felt briefly dizzy; it’s accompanied by palpitations, chest tightness, or shortness of breath; it started when you began a new medication; or you’re over 65 and it’s increasing your risk of falls. A GP can run a simple lying and standing blood pressure check to confirm the diagnosis. From there, depending on cause, options range from medication review to further investigation of autonomic function.

    The key thing is not to normalise it to the point of ignoring something that’s genuinely telling you something. A brief head rush on standing is common. Frequent, severe, or progressive episodes are not something to just live with.